Introduction
Neurodegenerative Diseases (NDDs) represent a broad class of progressive neurological disorders, including Parkinson’s Disease (PD), Huntington’s Disease (HD), and Amyotrophic Lateral Sclerosis (ALS) [ 1 ], characterized by progressive structural and functional degeneration of neurons, which ultimately lead to neuronal dysfunction and cell death [ 2 ]. Beyond their direct neurological impact, NDDs significantly impair individuals’ ability to perform daily activities and maintain independent living [ 3 - 6 ]. Motor dysfunction is one of the most prominent clinical manifestations of NDDs. In the early stages of PDs, patients commonly experience reduced movement speed, shortened stride length, diminished arm swing, and increased inter-limb asymmetry. HD is often associated with involuntary movements (chorea), gait instability, and balance impairment, while ALS primarily manifests as progressive muscle weakness, impaired speech and swallowing, and muscular tremors [ 6 - 9 ]. Compared with Healthy Control Group (HC), who demonstrate natural and symmetric coordination between the lower limbs, patients with NDDs exhibit disrupted inter-limb coordination and impaired motor synchronization during gait. These abnormalities indicate that gait dynamics provide a sensitive and reliable window into neuromotor dysfunction. Consequently, analysis of lower-limb coordination and gait time-series dynamics offers a powerful and non-invasive approach for detecting motor impairments associated with neurodegenerative diseases.
Currently, conventional diagnostic methods for progressive neurological disorders, such as genetic testing and neuroimaging, are widely used in clinical practice [ 4 , 10 ]. Although these approaches provide valuable diagnostic information, they are often costly, invasive, time-consuming, and in some cases insufficiently sensitive for early-stage diagnosis. As a result, there has been growing interest in the development of rapid, low-cost, and non-invasive diagnostic tools that are suitable for clinical and screening environments [ 11 , 12 ]. Among these approaches, gait analysis has emerged as a particularly promising modality, as gait signals can non-invasively capture pathological motor patterns associated with neurodegenerative diseases [ 13 , 14 ].
Motor impairments associated with neurological disorders are typically progressive and worsen over time, leading to increasing gait disturbances, postural instability, and functional disability [ 3 - 6 ]. Early diagnosis of neuromotor disorders is therefore essential, not only for slowing disease progression but also for optimizing therapeutic interventions and improving patients’ quality of life [ 15 - 18 ]. In this context, advanced computational methods, particularly artificial intelligence–based techniques, have shown strong potential for supporting clinical diagnosis, especially when symptoms are mild, and early-stage clinical assessment is challenging. These approaches enable automated pattern recognition in complex gait data and facilitate objective, reproducible classification of disease-related motor abnormalities.
Recent studies have introduced a wide range of machine learning–based frameworks for classifying NDDs using gait signal analysis, feature extraction techniques, and statistical learning models. These methods typically rely on long-duration gait recordings and multi-stage signal processing pipelines to achieve robust and reliable classification performance.
Yang et al. [ 19 ] normalized the temporal gait cycle data stance and swing phases of both legs and extracted features, such as maximum signal-to-noise ratio and signal-to-noise ratio with minimum correlation, and maximum predictive power with minimum correlation. The selected features, obtained via principal component analysis, were then applied to a Support Vector Machine (SVM) classifier with 10-fold cross-validation. The results demonstrated that the two classes (diseased and healthy) were distinguished with an average accuracy of 86.85%. Iram et al. [ 20 ] examined features, such as age, gender, height, weight, gait speed, disease severity, and body mass index for 10 individuals across different groups, including Parkinson’s, Huntington’s, ALS, and healthy controls. After applying various classical classifiers, the best performance was reported by the Bayesian classifier with an average accuracy of 65% [ 20 ].
Banaie et al. [ 21 ] extracted features, such as mean, zero-crossing rate, and standard deviation from the step-by-step gait time series of 62 individuals (16 healthy controls, 19 with Huntington’s Disease, 14 with Parkinson’s Disease, and 13 with ALS). After classifying these features using various classical classifiers, the highest accuracy was achieved with the quadratic Bayesian classifier, yielding an average accuracy of 86.95%. Sanchez-DelaCruz et al. [ 22 ] followed a similar approach. In their experiment, they first used 13 features and later repeated the classification process with a selection of 5 different features. They employed one-vs-one and one-vs-all classification strategies and split the data into two-thirds for training and one-third for testing. The results showed that the classification accuracy across different groups ranged between 65% and 96.83%. Rehman et al. [ 23 ] extracted five clinical gait features: step length variability, mean step width, mean step length, mean step speed, and step width variability. Using a SVM classifier, the classification accuracy for distinguishing PD from healthy individuals ranged from 73% to 97%, depending on the selected features.
Das et al. [ 24 ] employed fast Fourier transform and power spectral density methods to compute the frequency spectrum of the left step, right step, and left swing phase of individuals from neurodegenerative disease groups. The data were divided into ten segments, and features, such as mean, variance, skewness, and kurtosis were extracted from each segment. These features were then fed into three different classifiers: an artificial neural network with an accuracy of 90.6%, SVM with 64% accuracy, and Bayesian classifier with 44.44% accuracy. Wahid et al. [ 25 ] utilized spatiotemporal gait features and machine learning algorithms to detect gait patterns of individuals with PD and Healthy Controls. After normalizing the data using multiple regression, subject selection was performed based on patient attributes, such as age, height, gender, body mass index, and preferred walking speed. The results showed that the random forest classifier achieved the highest discriminative power with an accuracy of 92.6%, followed by SVM with 80.4% and the Fisher linear discriminant with 86.2% accuracy for distinguishing between PD and HC groups.
Ye et al. [ 26 ] utilized temporal gait features in conjunction with an adaptive neuro-fuzzy inference system optimized by a particle swarm optimization algorithm to classify patients with neurodegenerative diseases. The classification accuracies reported for distinguishing NDD vs. HC, ALS vs. HC, PD vs. HC, and HD vs. HC were 90.63%, 93.10%, 90.22%, and 94.44%, respectively. Elden et al. [ 27 ] employed both linear and nonlinear features extracted from the time series of the right foot’s stance phase and the double stance phase. The nonlinear features included permutation entropy and approximate entropy, while the linear features included autocovariance and the root mean square as a statistical feature. The evaluation results using an SVM classifier yielded accuracies of 90.62% for NDD vs. HC, 96.43% for ALS vs. PD, 91.90% for ALS vs. HD, and 94.28% for PD vs. HD. Prasanna et al. [ 28 ] proposed a nonlinear feature extraction method for classifying healthy individuals and NDD patients. To calculate step fluctuations, they utilized logarithmic energy entropy and extracted statistical features, such as minimum, maximum, mean, and normalized energy. Using an artificial neural network classifier, the best accuracy of 93.5% was achieved for classifying PD versus healthy controls.
Monfared and Maleki [ 1 ] implemented a quantitative recursive analysis method on the time series of swing, step, and stance intervals. They then extracted the most effective features using the sequential floating forward search algorithm and performed a four-class classification among normal, ALS, HD, and PD groups, with an accuracy of 87.9%.
Recent studies [ 1 , 20 - 28 ] have mainly evaluated five-minute (approximately 300 seconds) walking recordings. In contrast, the present study focuses on the analysis of only two consecutive gait steps, corresponding to approximately one second of the walking cycle. Moreover, previous research has primarily emphasized binary classification tasks, such as distinguishing a single neurodegenerative disease from healthy controls. In this study, both multiple binaries and a four-class classification framework are investigated.
The aim of this research is to develop an efficient and rapid diagnostic system for detecting neurodegenerative diseases and identifying specific disease types using only two consecutive steps extracted from short-term gait time-series signals. This short-time analysis framework is designed to enable early diagnosis, reduce data acquisition time, minimize patient burden, and support practical clinical deployment.
Material and Methods
This analytical study aimed at short-term identification of neurodegenerative diseases using publicly available gait datasets from PhysioNet. Figure 1 illustrates a schematic overview of the workflow, including the database, preprocessing, feature vector construction, and classification. Time-series data of stride, stance, and swing phases from both legs during walking of 64 participants from patient and healthy groups were utilized. By applying preprocessing procedures on the individuals’ time-series data, more precise information was extracted. Then, to simplify and focus on specific and meaningful patterns in the dynamic gait cycle signals, only two consecutive steps from each individual were selected for analysis. These two steps were then converted into a feature vector, which served as input for the classification models to distinguish patients with NDDs from healthy participants and differentiate among three specific disease classes. Various efficient machine learning algorithms were employed, and quantitative accuracy metrics were used to evaluate the models’ performance. Each step of this workflow is described in detail in the following sections.
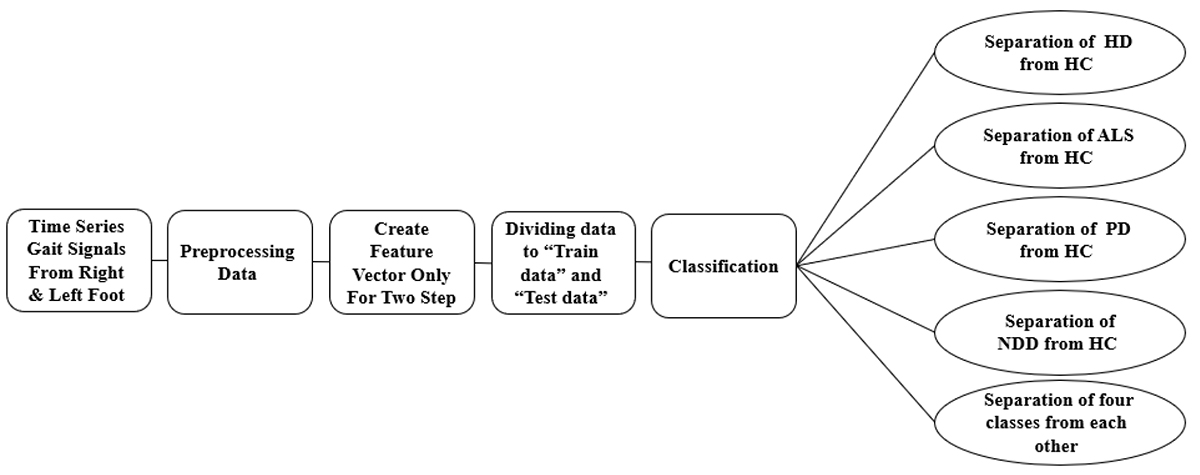
Figure 1. The Flowchart of the proposed method for diagnosing progressive neurodegenerative diseases. (PD: Parkinson’s Disease, HD: Huntington’s Disease, ALS: Amyotrophic Lateral Sclerosis, HC: Healthy Controls, NDD: Neurodegenerative Diseases)
Neuro-Degenerative Diseases Database
To implement the proposed method, a dataset was utilized to analyze gait dynamics in neurodegenerative disorders [ 29 ]. The dataset includes information from 64 individuals, comprising 16 healthy controls (14 females and 2 males; ages 20 to 74 years), 20 patients with HD (13 females and 7 males; ages 29 to 71 years), 15 PD patients (5 females and 10 males; ages 44 to 80 years), and 13 patients with ALS (3 females and 10 males; ages 36 to 70 years). The data were recorded during 5 minutes of walking and include force signals from the left and right feet along with 12 temporal features extracted from gait cycles [ 30 ]. These features consist of the step, swing, and stance time of both legs, as well as the double support time (expressed in seconds and as a percentage of the gait cycle) [ 31 ]. In this study, all the time-series features were employed.
Signal Preprocessing
To reduce the impact of artifacts caused by movement initiation and termination transitions, the first and last 15 seconds of the dataset were removed in accordance with previous methods by Hausdorff et al. [ 32 , 33 ]. The necessity of this removal stems from instability or the lack of consistency during the initial and final time intervals of movement. Subsequently, to enhance signal quality and eliminate abnormal fluctuations or outliers, a median filter was applied, designed to remove values that were greater or smaller than three times the standard deviation from the mean of the data [ 34 , 35 ]. The use of this filter effectively eliminated signals resulting from sudden and irregular movements, leaving only the genuine changes in individuals’ movement status. This process was particularly capable of identifying abrupt changes in movement patterns, which significantly contributed to more accurate simulation and analysis of patients with motor disorders.
Feature Vector Creation
To facilitate analysis and reduce computational complexity, instead of using the entire 300-second walking samples, which may involve complex and time-consuming analysis, only two consecutive steps, equivalent to approximately one second of the natural walking cycle, were considered. To maximize the optimal utilization of the available time-series data, the entire pre-processed gait signal was systematically segmented into consecutive and non-overlapping two-step windows. This segmentation process yielded multiple short-term samples (each approximately one second in duration) from the gait dynamics of every subject (or participant). Consequently, the total dataset employed for classification comprised 7,580 two-step samples. The distribution of these samples across the classes is as follows: 1,844 samples from PD, 2,423 from HD, 1,275 from ALS, and 2,038 from HC. This short-time selection was particularly made because two consecutive steps can represent critical motor changes in the walking process while avoiding redundant and excessive information. Therefore, the extracted feature vector includes temporal information related to the individuals’ gait cycle within this short one-second interval. By limiting the data to two steps, more precise and faster analyses can be performed. The extracted short-time time-series features were then prepared as input for various classification algorithms.
Classification
A four-class classification framework was implemented to differentiate healthy controls from patients with PD, HD, and ALS using multiple classifiers. To perform this classification task, a diverse set of linear, nonlinear, and ensemble classifiers was applied to evaluate their performance in accurately classifying these groups. Linear Discriminant Analysis (LDA) was used as a linear classifier due to its simple structure and high interpretability, making it suitable for classification problems with linearly separable boundaries. Among nonlinear classifiers, logistic regression, kernel-based naive Bayes, SVM with Gaussian kernels, SVM with nonlinear kernels, weighted k-nearest neighbors, decision trees, and multilayer perceptron neural networks were utilized. These classifiers are more effective in handling complex and nonlinear data by modeling intricate decision boundaries. Additionally, an ensemble classifier based on bagging trees was applied, which combines multiple base models to reduce variance and increase stability, thereby providing improved performance.
In this study, the Bagged Trees ensemble model consisted of 100 CART decision trees as base learners, using the Gini index as the splitting criterion. Bootstrap sampling with replacement was enabled, the minimum leaf size was set to one, no maximum tree depth was imposed, and majority voting was used as the aggregation method. Out-of-bag prediction was disabled, and no hyperparameter optimization was applied. Besides evaluating the classifiers’ performance in four-class classification, four binary classification scenarios were also tested to assess the accuracy of distinguishing specific groups. These scenarios included ALS vs. HC, PD vs. HC, HD vs. HC, NDD vs. HC, as well as the four-class classification among ALS, PD, HD, and HC.
Cross Validation
To evaluate the performance of classifiers, a 4-fold cross-validation technique was employed. To prevent the significant risk of data leakage and ensure the external validity (generalization ability) of our findings, the cross-validation procedure was strictly implemented using a subject-wise split. This methodological requirement dictates that all two-step samples extracted from a single subject were treated as an indivisible unit and assigned exclusively to either the training or the test set within any given fold. This rigorous, subject-level division guarantees that the model’s performance is assessed only on data from entirely unseen individuals, thereby providing an unbiased and robust measure of classification accuracy. In this method, the dataset is divided into four equal parts, and the model is consecutively trained four times; in each iteration, one part is used as the test data while the remaining parts serve as the training data. This process ensures that each sample appears at least once in the test data, resulting in a more accurate assessment of the model’s performance. After completing all iterations, the average of the results from the four folds is reported as the final performance metric of the model. Cross-validation prevents overfitting and ensures the model’s generalizability to new data, thereby enabling a more precise evaluation of the classifiers.
Quantitative Evaluation Metric
To evaluate model performance, classification accuracy was used as the evaluation metric. Accuracy was defined as the ratio of correctly classified samples to the total number of samples, and was also computed from the confusion matrix using True Positive (TP), True Negative (TN), False Positive (FP), and False Negative (FN), as shown in Equation (1).
Results
The use of a short time window consisting of two consecutive steps enables early detection of patients with progressive neurological disorders. Table 1 shows the classification accuracy for two-class and four-class classifiers. The lowest accuracy belongs to the linear LDA classifier, as LDA is a linear method and cannot effectively capture nonlinear relationships between features and classes. In contrast, the highest accuracy was achieved by the Ensemble classifier. This model’s superior performance is attributed to its ability to model complex nonlinear relationships, create wider decision margins between classes, resist noisy data, and offer high flexibility in kernel selection and parameter tuning. The results showed that the Ensemble classifier, with an accuracy of 82.8%, significantly outperformed other models in simulating the proposed method. Additionally, this model demonstrated high accuracy in discriminating ALS vs. HC (97.6%), NDD vs. HC (89.1%), PD vs. HC (90%), and HD vs. HC (88.4%). Moreover, the multilayer perceptron neural network also exhibited reasonable performance, though with lower accuracy.
| Classification | PD vs HC | HD vs HC | ALS vs HC | NDD vs HC | ALS vs PD vs HD vs HC |
|---|---|---|---|---|---|
| Linear Discriminant | 74 | 63.9 | 93 | 80 | 45 |
| Logistic Regression Kernel | 75 | 74 | 78 | 79 | 58.6 |
| Kernel Naive Bayes | 81.9 | 74.9 | 89.4 | 79 | 61 |
| Fine Gaussian SVM | 91.6 | 89 | 96.2 | 86 | 72.3 |
| Weighted KNN | 90.1 | 85.1 | 97.5 | 86 | 71.9 |
| Fine Tree | 86 | 83 | 93 | 85 | 63.9 |
| Neural Network | 88 | 86.1 | 97 | 88 | 80 |
| SVM Kernel | 77.1 | 76 | 80.2 | 81.7 | 75 |
| Multi Layer Perceptron | 84.9 | 76.3 | 95.9 | 88 | 79 |
| Ensemble (Bagged Trees) | 90 | 88.4 | 97.6 | 89.1 | 82.8 |
| PD: Parkinson’s Disease, HC: Healthy Controls, HD: Huntington’s Disease, ALS: Amyotrophic Lateral Sclerosis, NDD: Neurodegenerative Diseases, SVM: Support Vector Machine, KNN: K-Nearest Neighbors | |||||
Table 2 compares the results of the proposed method using a combined classifier with previous studies. Recent articles on neurodegenerative disease classification have typically used 300 seconds of gait data, which is considered a long-time window for walking data collection. In contrast, this study analyzes only two consecutive steps approximately one second of individual movement as input. This novel approach is introduced as a short-time diagnostic solution for simulating motor disorders. Compared to previous studies [ 19 , 22 , 26 ] that primarily focused on classifying NDD groups versus HC, the findings indicate no significant decrease in classification accuracy despite using short-time signals. Specifically, the accuracy of distinguishing ALS from HC is significantly higher than those of these studies. Furthermore, the proposed method shows improvements in classifying HD vs. HC and PD vs. HC compared to studies [ 19 - 22 ]. Unlike previous studies that used long-term recordings (e.g., 300 seconds), this study showed that short-term (one second) recordings of the gait cycle (two consecutive steps) allow for faster and more accurate classification of neurodegenerative diseases.
| Author | Elapsed Time (seconds) | PD vs HC | HD vs HC | ALS vs HC | NDD vs HC |
|---|---|---|---|---|---|
| Monfared Jahromi et al. [1] | 300 | 93.10 | 92 | 96.20 | 91.70 |
| Yang et al. [19] | 300 | 86.43 | 84.17 | 93.96 | 86.85 |
| Iram et al. [20] | 300 | - | - | - | 65 |
| Banaei et al. [21] | 300 | 80 | 71.42 | 100 | 86.95 |
| Sanchez-DelaCruz et al. [22] | 300 | 76 | 71 | 84 | 81 |
| Das et al. [24] | 300 | - | - | - | 90.6 |
| Wahid et al. [25] | 300 | 92.6 | - | - | - |
| Ye et al. [26] | 300 | 90.22 | 94.44 | 93.10 | 90.63 |
| Elden et al. [27] | 300 | - | - | - | 90.62 |
| Prasanna et al. [28] | 300 | 93.5 | - | - | - |
| Proposed work | ≈ 1 | 90 | 88.4 | 97.6 | 89.1 |
| PD: Parkinson’s Disease, HC: Healthy Controls, HD: Huntington’s Disease, ALS: Amyotrophic Lateral Sclerosis, NDD: Neurodegenerative Diseases | |||||
Discussion
This study demonstrates that diagnostically relevant information for neurodegenerative disease classification can be reliably extracted from extremely short gait segments consisting of only two consecutive steps (≈1 s). Experimental results confirm that short-term gait dynamics contain sufficient discriminative information to support both binary and multiclass classification tasks. Among the evaluated models, the ensemble classifier (bagged trees) achieved the best overall performance, highlighting the effectiveness of nonlinear ensemble learning for capturing the complex, nonstationary characteristics of pathological gait patterns.
Linear classifiers, such as LDA, showed weaker performance, indicating that linear decision boundaries are insufficient to model the high-dimensional inter-limb coordination, temporal variability, and nonlinear motor control alterations associated with neurodegenerative diseases. In contrast, ensemble methods integrate multiple nonlinear decision structures, providing more robust modeling of complex gait patterns and improved generalization across disease classes.
The main contribution of this study is the achievement of classification performance comparable to long-term protocols using very short-term recordings. Previous studies [ 1 , 19 - 28 ] typically relied on 5-minute walking sessions (≈300 s) to extract discriminative features. Our findings show that essential disease-related motor signatures are embedded in fine-scale temporal dynamics, which can be captured in very short time windows. This indicates that pathological neuromotor alterations manifest as micro-scale temporal irregularities, coordination deficits, and nonlinear variability patterns detectable in short-term gait segments.
A quantitative comparison with recent studies further highlights the effectiveness of the proposed short-time framework. Overall, the classification performance of this study is comparable to or better than most state-of-the-art studies while using short-term (about one second) data from gait recordings rather than the long-term (about 300 seconds) recordings used in previous studies. For ALS vs. HC classification, our proposed method achieved higher accuracy than most previous studies. The only exception is the study by Banaei et al. [ 21 ], which reported an accuracy of approximately 2.4% higher than our method. Although Sanchez-DelaCruz et al. [ 22 ] shows an improvement of approximately 13.6% in ALS vs. HC classification accuracy using our framework. For PD vs. HC and HD vs. HC classification, the results are competitive with those reported in studies [ 19 - 22 ], showing either higher performance or only marginal differences. In studies such as [ 24 ] and [ 27 ], the performance differences for NDD vs HC remain within a narrow margin of less than 0.6%, and in study [ 25 ], PD vs HC remains within 2.6%, indicating comparable discriminative capability. These findings are particularly noteworthy given the drastic reduction in data length, confirming that short-time gait dynamics preserve sufficient pathological information for reliable diagnosis and classification of neurodegenerative motor disorders.
From a clinical perspective, the short-time analysis paradigm offers several advantages. Reduced data acquisition time minimizes patient burden and fatigue, especially for those with severe motor impairments or limited walking endurance. It also enables rapid screening and assessment protocols, increasing feasibility in real-world clinical environments. Furthermore, the framework can be integrated with low-cost, non-invasive sensing technologies, facilitating scalable and accessible deployment.
Despite these promising results, several limitations should be noted. The study used a relatively small public dataset with limited participant diversity, which may affect generalizability. Class imbalance at both participant and sample levels may introduce bias. Additionally, the lack of disease-stage information limits evaluation across progression stages. Finally, data were collected under controlled laboratory conditions with force sensors, leaving uncertainty about applicability in real-world settings. Validation using wearable sensors, smartphones, inertial measurement units or marker-free motion capture systems (e.g., Microsoft Kinect) is needed to confirm robustness and generalizability.
Conclusion
This study presents a short-time gait analysis framework for the classification of neurodegenerative diseases based on only two consecutive steps. By leveraging time-domain gait dynamics and classical machine learning models, the approach achieves high diagnostic performance across both binary and multiclass classification tasks. The ensemble (bagged trees) classifier consistently demonstrates the strongest performance, confirming the importance of nonlinear and ensemble learning strategies for modeling complex pathological gait patterns.
Unlike conventional methods requiring long-duration gait recordings, the proposed framework demonstrates that reliable diagnostic information can be extracted from ultra-short gait segments. This substantially reduces data acquisition time, minimizes patient burden, and enables rapid, non-invasive clinical assessment. The findings establish short-term gait dynamics as a robust biomarker for early detection and classification of neurodegenerative diseases. Overall, the two-step gait analysis framework offers a practical, efficient, and clinically applicable solution for rapid neurodegenerative disease screening, with strong potential for integration into real-world diagnostic workflows and clinical decision-support systems.
Authors’ Contribution
N. Monfared Jahromi contributed to conceptualization, formal analysis, investigation, methodology, visualization, and writing original draft preparation. A. Maleki contributed to conceptualization, investigation, project administration, validation, and writing, review and editing. All the authors read, modified, and approved the final version of the manuscript.
Ethical Approval
This study used publicly available datasets on the PhysioNet website and did not involve the collection of new data from human participants or animals. Ethical approval was not required as all data were anonymized and publicly accessible.
Funding
The authors received no specific funding for this work.
Conflict of Interest
None
References
- Monfared Jahromi N, Maleki A. Classification of Neurodegenerative Diseases Using Recurrence Quantification Analysis of Gait Signal. Iran J Biomed Eng. 2025; 19(2):125-36. DOI
- Lewis PA, Spillane JE. The molecular and clinical pathology of neurodegenerative disease. Academic Press; 2018.
- Prabhu P, Karunakar AK, Anitha H, Pradhan N. Classification of gait signals into different neurodegenerative diseases using statistical analysis and recurrence quantification analysis. Pattern Recognit Lett. 2020; 139:10-6. DOI
- Saljuqi M, Ghaderyan P. Detection of neurodegenerative diseases using time-frequency symmetric features of gait signal. Iran J Biomed Eng. 2021; 15(1):59-71. DOI
- Renjewski D, Lipfert S, Günther M. Foot function enabled by human walking dynamics. Phys Rev E. 2022; 106(6-1):064405. DOI | PubMed
- Chaki J, Woźniak M. Deep learning for neurodegenerative disorder (2016 to 2022): A systematic review. Biomed Signal Process Control. 2023; 80:104223. DOI
- Dutton M. Physical Therapist Assistant Exam Review Guide. Jones & Bartlett Learning; 2012.
- Takashima R, Murata W, Saeki K. Movement changes due to hemiplegia in stroke survivors: a hermeneutic phenomenological study. Disabil Rehabil. 2016; 38(16):1578-91. DOI | PubMed
- Banaie M, Sarbaz Y, Gharibzadeh S, Towhidkhah F. Huntington’s disease: modeling the gait disorder and proposing novel treatments. J Theor Biol. 2008; 254(2):361-7. DOI | PubMed
- De Bie RMA, Katzenschlager R, Swinnen BEKS, Peball M, Lim SY, Mestre TA, et al. Update on Treatments for Parkinson’s Disease Motor Fluctuations - An International Parkinson and Movement Disorder Society Evidence-Based Medicine Review. Mov Disord. 2025; 40(5):776-94. Publisher Full Text | DOI | PubMed [ PMC Free Article ]
- Joshi D, Khajuria A, Joshi P. An automatic non-invasive method for Parkinson’s disease classification. Comput Methods Programs Biomed. 2017; 145:135-45. DOI | PubMed
- Xia Y, Gao Q, Lu Y, Ye Q. A novel approach for analysis of altered gait variability in amyotrophic lateral sclerosis. Med Biol Eng Comput. 2016; 54(9):1399-408. DOI | PubMed
- Gómez-Río M, Caballero MM, Górriz Sáez JM, Mínguez-Castellanos A. Diagnosis of Neurodegenerative Diseases: The Clinical Approach. Curr Alzheimer Res. 2016; 13(5):469-74. DOI | PubMed
- Andriacchi TP, Alexander EJ. Studies of human locomotion: past, present and future. J Biomech. 2000; 33(10):1217-24. DOI | PubMed
- National Collaborating Centre for Chronic Conditions (UK). Parkinson’s Disease: National Clinical Guideline for Diagnosis and Management in Primary and Secondary Care. London: Royal College of Physicians (UK) ; 2006.
- Soubra R, Chkeir A, Novella JL. A Systematic Review of Thirty-One Assessment Tests to Evaluate Mobility in Older Adults. Biomed Res Int. 2019; 2019:1354362. Publisher Full Text | DOI | PubMed [ PMC Free Article ]
- Frank S, Jankovic J. Advances in the pharmacological management of Huntington’s disease. Drugs. 2010; 70(5):561-71.
- Aydin F, Aslan Z. Classification of neurodegenerative diseases using machine learning methods. Int J Intell Syst Appl Eng. 2017; 1(5):1-9. DOI
- Yang M, Zheng H, Wang H, McClean S. Feature selection and construction for the discrimination of neurodegenerative diseases based on gait analysis. 3rd International Conference on Pervasive Computing Technologies for Healthcare; London, UK: IEEE; 2009.
- Iram S, Al-Jumeily D, Fergus P, Randles M, Hussain A. Computational data analysis for movement signals based on statistical pattern recognition techniques for neurodegenerative diseases. 13th Annual Post Graduate Symposium on the Convergence of Telecommunications, Networking and Broadcasting; Liverpool John Moores University; 2012. p. 1-6.
- Banaie M, Pooyan M, Mikaili M. Introduction and application of an automatic gait recognition method to diagnose movement disorders that arose of similar causes. Expert Syst Appl. 2011; 38(6):7359-63. DOI
- Sanchez-DelaCruz E, Parra PP. Machine learning-based classification for diagnosis of neurodegenerative diseases. LANMR; 2018. p. 40-50.
- Rehman RZU, Del Din S, Guan Y, Yarnall AJ, Shi JQ, Rochester L. Selecting Clinically Relevant Gait Characteristics for Classification of Early Parkinson’s Disease: A Comprehensive Machine Learning Approach. Sci Rep. 2019; 9(1):17269. Publisher Full Text | DOI | PubMed [ PMC Free Article ]
- Das KD, Saji AJ, Kumar CS. Frequency analysis of gait signals for detection of neurodegenerative diseases. International conference on circuit, power and computing technologies (ICCPCT); Kollam, India: IEEE; 2017.
- Wahid F, Begg RK, Hass CJ, Halgamuge S, Ackland DC. Classification of Parkinson’s Disease Gait Using Spatial-Temporal Gait Features. IEEE J Biomed Health Inform. 2015; 19(6):1794-802. DOI | PubMed
- Ye Q, Xia Y, Yao Z. Classification of Gait Patterns in Patients with Neurodegenerative Disease Using Adaptive Neuro-Fuzzy Inference System. Comput Math Methods Med. 2018; 2018:9831252. Publisher Full Text | DOI | PubMed [ PMC Free Article ]
- Elden RH, Ghoneim VF, Al-Atabany W. A computer aided diagnosis system for the early detection of neurodegenerative diseases using linear and non-linear analysis. 4th Middle East Conference on Biomedical Engineering (MECBME); Tunis, Tunisia: IEEE; 2018.
- Prasanna J, George ST, Subathra MS. Classification of gait signals for detection of neurodegenerative diseases using log energy entropy and ANN classifier. In Computational Techniques in Neuroscience; CRC Press; 2023. p. 101-12.
- Hausdorff JM, Ladin Z, Wei JY. Footswitch system for measurement of the temporal parameters of gait. J Biomech. 1995; 28(3):347-51. DOI | PubMed
- Monfared N, Maleki A. Short-time Classification of Neurodegenerative Diseases Based on Cross-Recurrence Quantification Analysis and Statistical Features. MSEEE. 2025; 5(3):1-11. DOI
- Hausdorff JM, Mitchell SL, Firtion R, Peng CK, Cudkowicz ME, Wei JY, et al. Altered fractal dynamics of gait: reduced stride-interval correlations with aging and Huntington’s disease. J Appl Physiol. 1997; 82(1):262-9. DOI | PubMed
- Hausdorff JM, Lertratanakul A, Cudkowicz ME, Peterson AL, Kaliton D, Goldberger AL. Dynamic markers of altered gait rhythm in amyotrophic lateral sclerosis. J Appl Physiol. 2000; 88(6):2045-53. DOI | PubMed
- Hausdorff JM, Cudkowicz ME, Firtion R, Wei JY, Goldberger AL. Gait variability and basal ganglia disorders: stride-to-stride variations of gait cycle timing in Parkinson’s disease and Huntington’s disease. Mov Disord. 1998; 13(3):428-37. DOI | PubMed
- Wu Y, Krishnan S. Statistical analysis of gait rhythm in patients with Parkinson’s disease. IEEE Trans Neural Syst Rehabil Eng. 2010; 18(2):150-8. DOI
- Yan Y, Ivanov K, Mumini Omisore O, Igbe T, Liu Q, Nie Z, Wang L. Gait Rhythm Dynamics for Neuro-Degenerative Disease Classification via Persistence Landscape- Based Topological Representation. Sensors (Basel). 2020; 20(7):2006. Publisher Full Text | DOI | PubMed [ PMC Free Article ]

